


PCSK9 inhibitors are injectable prescription cholesterol medications. On average they lower LDL cholesterol by 50–60% when added to statin therapy—enough to move many high-risk patients into a safer range. This guide compares Repatha (evolocumab) and Praluent (alirocumab) on effectiveness, dosing, cardiovascular outcomes, annual cost, and alternatives.
Quick Verdict
PCSK9 inhibitors typically lower LDL cholesterol by 50–60% when added to a statin, with some patients seeing reductions above 70%. Repatha (evolocumab) averages slightly higher LDL lowering in many studies—roughly 55–61%—while Praluent (alirocumab) averages around 45–50%, with a range of 36–59% in FDA-reviewed trials. Both drugs also reduce cardiovascular events in patients with established heart disease.
For most buyers, the deciding factor is not effectiveness—it is cost, insurance coverage, dosing schedule, and tolerability. Repatha’s list price is approximately $6,900 per year, though a direct-to-consumer program offers it at about $239 per month for eligible cash-paying U.S. patients. Praluent’s U.S. annual price has been reduced to roughly $5,850–$6,900, depending on dose and program.
These are not first-line cholesterol treatments. They are generally considered for people with familial hypercholesterolemia or established atherosclerotic cardiovascular disease who still need substantial LDL lowering despite maximally tolerated statin therapy. They do not replace statins, ezetimibe, diet, or lifestyle changes, and they require a prescription and medical monitoring.
Struggling to Keep Your Cholesterol in Check? Start With What Goes Into Your Body Every Day
Prescription therapy does the heavy lifting—but a daily heart-health supplement is one of the simplest habits you can add alongside it. This is the option our readers click on most.

- Built for a daily routine — easy to stack alongside diet, exercise, and prescribed therapy.
- Fully transparent label — view the complete ingredient panel before you decide.
- No prescription required — order directly and have it delivered to your door.
- Real customer feedback — read verified reviews and current ratings on Amazon.
- Price checked at the source — see today’s live price, not last month’s.
Live pricing and availability on Amazon · View current customer reviews
Please read: This is a dietary supplement, not a prescription medication. It is not FDA-approved to treat high cholesterol, prevent heart disease, or replace PCSK9 inhibitors, statins, ezetimibe, or any other prescribed therapy. We have not independently tested this product. Verify the current label, ingredient amounts, and warnings on Amazon, and speak with your healthcare professional before adding any supplement—especially if you take prescription medication.
1. What Are PCSK9 Inhibitors?
PCSK9 stands for proprotein convertase subtilisin/kexin type 9. It is a protein made by the liver that binds to LDL receptors and promotes their destruction. When LDL receptors are reduced, the liver clears less LDL cholesterol from the blood, and LDL levels rise.
PCSK9 inhibitors block this process. By preventing PCSK9 from destroying LDL receptors, they allow the liver to clear more LDL cholesterol from circulation. The result is a substantial drop in blood LDL levels—typically far beyond what statins alone can achieve.
There are three main PCSK9-targeting therapies currently approved in the United States:
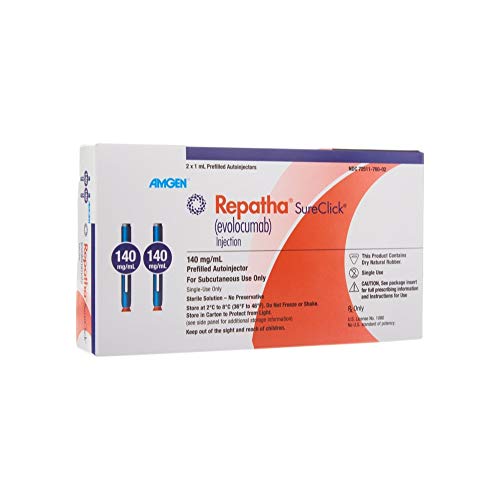
- Evolocumab (Repatha) — a monoclonal antibody given every 2 weeks or monthly.
- Alirocumab (Praluent) — a monoclonal antibody given every 2 or 4 weeks.
- Inclisiran (Leqvio) — a small interfering RNA therapy given twice yearly after initial dosing.
This article focuses on Repatha and Praluent because they are the two most commonly compared PCSK9 inhibitor injections.
2. How Much Do PCSK9 Inhibitors Lower Cholesterol?
The short answer: Most patients experience a 50–60% reduction in LDL cholesterol when a PCSK9 inhibitor is added to statin therapy. Individual results vary based on the specific drug, dose, baseline LDL level, adherence, and whether the patient has familial hypercholesterolemia.
Evolocumab (Repatha)
- Average LDL reduction: approximately 55–61% in major studies.
- FDA-reviewed data: in a 12-week study of patients with heterozygous familial hypercholesterolemia, Repatha produced an average LDL reduction of approximately 60% compared with placebo.
- Range: some analyses report reductions from the low 50s to the low 70s, depending on population and background therapy.
Alirocumab (Praluent)
- Average LDL reduction: approximately 45–50%.
- FDA-reviewed data: across five placebo-controlled trials, patients taking Praluent had an average LDL reduction ranging from 36% to 59% compared with placebo.
- Dose effect: higher doses and up-titration can push reductions toward the upper end of that range.
Why the Numbers Differ
The headline percentages come from different studies with different patient populations. A patient starting at an LDL of 150 mg/dL may experience a different absolute drop than a patient starting at 90 mg/dL, even if the percentage reduction is similar. What matters clinically is whether the patient reaches their LDL goal—often below 70 mg/dL, and sometimes below 55 mg/dL for very high-risk patients.
Key point: PCSK9 inhibitors are not interchangeable with statins. They are added on top of a maximally tolerated statin, and sometimes ezetimibe, when LDL remains above goal.
3. Repatha vs. Praluent: Effectiveness Compared
| Feature | Repatha (evolocumab) | Praluent (alirocumab) |
|---|---|---|
| Drug class | PCSK9 monoclonal antibody | PCSK9 monoclonal antibody |
| Typical LDL reduction | ~55–61% average; range up to ~70%+ | ~45–50% average; range 36–59% |
| Dosing | 140 mg SC every 2 weeks or 420 mg monthly | 75 mg or 150 mg SC every 2 weeks or 300 mg every 4 weeks |
| Cardiovascular outcomes trial | FOURIER: 15% relative risk reduction in MACE (HR 0.85) | ODYSSEY OUTCOMES: HR 0.85 for MACE |
| Approved for | Established CVD; primary hyperlipidemia including HeFH; HoFH; pediatric HeFH | Established CVD; primary hyperlipidemia including HeFH; pediatric HeFH |
| Injection-site reactions | ~2.1% vs. 1.6% placebo in FOURIER | ~7.2% vs. 5.1% in pooled trials |
| Head-to-head superiority | Not established—no major trial has shown one agent superior to the other for cardiovascular outcomes | |
Interpretation: Repatha tends to produce slightly larger average LDL reductions in many datasets, but the difference is modest and not consistent across every study. Praluent offers flexible dosing, including a once-monthly option. For most patients, the choice comes down to insurance coverage, out-of-pocket cost, dosing preference, and tolerability rather than a proven efficacy gap.
4. How Long Do They Take to Work?
PCSK9 inhibitors begin lowering LDL quickly. The LDL-lowering effect can typically be measured as early as 4 weeks after starting Repatha. Many clinicians recheck lipid panels at 4–8 weeks to assess response and decide whether dose adjustment or additional therapy is needed.
Maximum LDL reduction is usually seen within 2–3 months of consistent use. Because these are chronic medications, the benefit depends on continued adherence. Missing doses can cause LDL to rise again.
5. Beyond LDL: Do They Reduce Heart Attacks and Strokes?
Yes—in patients with established cardiovascular disease. This is a critical distinction. Lowering LDL is a surrogate marker; the reason to use these drugs is to reduce cardiovascular events.
FOURIER (evolocumab): In more than 27,000 patients with established cardiovascular disease on statin therapy, evolocumab reduced the risk of major cardiovascular events by 15% (HR 0.85) over a median follow-up of 26 months. The benefit was consistent across major subgroups.
ODYSSEY OUTCOMES (alirocumab): In patients who had a recent acute coronary syndrome, alirocumab reduced the risk of major cardiovascular events with a hazard ratio of 0.85—also a 15% relative risk reduction.
These outcome trials are why PCSK9 inhibitors are guideline-recommended for high-risk patients who need additional LDL lowering. They are not merely “cholesterol numbers” drugs; they have demonstrated event reduction in large randomized trials.
6. Cost Comparison: Repatha vs. Praluent
PCSK9 inhibitor pricing is complex. List prices, insurer-negotiated prices, patient-assistance programs, and cash-pay options can differ dramatically. The table below summarizes publicly reported figures, but prices change frequently and should be verified with the manufacturer, pharmacy, or insurer.
| Cost Category | Repatha (evolocumab) | Praluent (alirocumab) |
|---|---|---|
| Approximate annual list price | ~$6,900/year | ~$5,850–$6,900/year |
| Monthly list equivalent | ~$575/month | ~$490–$575/month |
| Direct-to-consumer / cash-pay program | ~$239/month through the manufacturer’s direct program for eligible U.S. patients paying cash | Cash-pay and manufacturer programs vary; check current availability |
| Commercial insurance copay card | May reduce cost to a low fixed monthly amount for eligible commercially insured patients; government plans excluded | Manufacturer copay programs may be available; eligibility varies |
| Medicare Part D | Many plans cover Repatha; roughly three-quarters of Medicare prescriptions reportedly cost patients about $50 or less per month | Coverage and tier placement vary by plan; check formulary |
| Prior authorization | Often required | Often required |
What the table does not capture:
- Deductibles, coinsurance, and specialty-tier pharmacy costs.
- Injection-training or administration fees, if applicable.
- Travel or time costs for appointments.
- The cost of managing side effects or monitoring.
Practical takeaway: The “sticker price” is rarely what insured patients pay. Manufacturer copay cards, patient-assistance programs, and Medicare Part D coverage can substantially reduce out-of-pocket costs. However, prior authorization is common, and not every patient qualifies for every program.
Compare available options and verify current pricing with your plan
7. Are PCSK9 Inhibitors Worth the Cost?
This is a nuanced question. From a pure cost-effectiveness standpoint, PCSK9 inhibitors are expensive relative to generic statins and ezetimibe. A 2026 systematic review reported incremental cost-effectiveness ratios (ICERs) of roughly $53,938–$117,551 per quality-adjusted life-year for alirocumab and $60,708–$165,689 for evolocumab—well above commonly cited U.S. willingness-to-pay thresholds of $100,000–$150,000 per QALY.
But cost-effectiveness is not the same as clinical value for an individual patient. For a patient with familial hypercholesterolemia or established cardiovascular disease who cannot reach LDL goals on statins and ezetimibe, a PCSK9 inhibitor may be the difference between ongoing elevated risk and meaningful LDL reduction. The drug may be “expensive” from a population-health perspective while still being “worth it” for a high-risk individual who otherwise has few options.
A practical framework:
- If you have established ASCVD or HeFH and your LDL remains above goal on maximally tolerated statin ± ezetimibe, a PCSK9 inhibitor is guideline-supported and may provide meaningful risk reduction.
- If you have not tried a high-intensity statin and ezetimibe, those lower-cost options should generally be optimized first.
- If cost is the main barrier, ask about manufacturer copay cards, patient-assistance programs, direct-to-consumer pricing, and alternative agents such as bempedoic acid or inclisiran.
8. Alternatives to PCSK9 Inhibitors
PCSK9 inhibitors are not the only non-statin options. The right choice depends on how much additional LDL lowering is needed, what the patient has already tried, and cost.
| Therapy | How it works | Typical additional LDL reduction | Cost profile | Key considerations |
|---|---|---|---|---|
| High-intensity statin | Blocks cholesterol synthesis in the liver | ~50% | Generic, low cost | First-line for most patients; muscle and liver monitoring |
| Ezetimibe | Blocks intestinal cholesterol absorption | ~20–25% | Generic, low cost | Often added before PCSK9 inhibitors |
| Bempedoic acid | Inhibits ATP citrate lyase in the liver | ~15–25% | Moderate cost | Oral; option for statin-intolerant patients |
| Inclisiran (Leqvio) | siRNA that reduces PCSK9 production | ~50–55% | ~$5,700/year | Twice-yearly maintenance dosing after initial doses |
| PCSK9 monoclonal antibodies (Repatha, Praluent) | Block circulating PCSK9 | ~50–60% | ~$5,850–$6,900/year list; assistance may lower | Injections every 2–4 weeks; outcome data available |
| Bile acid sequestrants | Bind bile acids in the gut | ~15–25% | Low–moderate | GI side effects; drug interactions |
For many patients, the practical sequence is: maximally tolerated statin → add ezetimibe → consider a PCSK9 inhibitor, bempedoic acid, or inclisiran depending on LDL goal, tolerability, and coverage.
9. Safety and Side Effects
PCSK9 inhibitors are generally well tolerated in clinical trials. The most common side effects are injection-site reactions, such as redness, swelling, or pain at the injection site. In the FOURIER trial, injection-site reactions occurred in 2.1% of patients taking evolocumab versus 1.6% taking placebo, and most were mild. Pooled alirocumab trials have reported injection-site reactions in roughly 7.2% of patients versus 5.1% with placebo.
Other reported adverse effects include:
- Nasopharyngitis (common cold symptoms)
- Headache
- Back pain
- Diarrhea or nausea
- Rare hypersensitivity reactions
Important safety notes:
- PCSK9 inhibitors are contraindicated in patients with a history of serious hypersensitivity to the drug or its components.
- They should not be used as a substitute for statins in patients who can tolerate statins.
- They are not approved for use in pregnancy without a careful risk–benefit discussion.
- Long-term safety data continue to accumulate; patients should be monitored by a clinician.
10. Who Is a Candidate?
PCSK9 inhibitors are generally considered for:
- Adults with heterozygous familial hypercholesterolemia (HeFH) who need additional LDL lowering despite maximally tolerated statin therapy.
- Adults with homozygous familial hypercholesterolemia (HoFH) — Repatha is approved for this indication.
- Adults with established atherosclerotic cardiovascular disease (ASCVD)—such as prior heart attack, stroke, or peripheral artery disease—who remain above LDL goal on statin ± ezetimibe.
- Some pediatric patients with HeFH, depending on age and product labeling.
They are not typically first-line therapy for otherwise healthy adults with mildly elevated cholesterol. Lifestyle changes, statins, and ezetimibe remain the foundation of cholesterol management for most people.
11. Heart-Healthy Lifestyle Support
Affiliate Disclosure: The links below are affiliate links. We may earn a commission if you purchase through them, at no additional cost to you. These products are dietary supplements, not prescription medications. They are not FDA-approved to treat high cholesterol, prevent heart disease, or replace PCSK9 inhibitors, statins, or any other prescribed therapy. Always check current ingredients, serving sizes, and warnings on Amazon, and speak with your healthcare professional before adding any supplement—especially if you take prescription medication.
If you are already working with a clinician on a cholesterol-lowering plan, you may also be building a heart-healthy daily routine that includes diet, exercise, sleep, and—for some people—dietary supplements. The options below are among the heart-health products readers frequently ask about. We have not independently tested these products, and the links resolve to Amazon listings where you can verify the current label, price, and customer reviews.
⭐ Our Most-Clicked Heart-Health Pick
Readers keep coming back to this one. View the full ingredient panel, serving size, live pricing, and verified customer reviews directly on Amazon before you decide.
Featured Heart-Health Supplement
Verify current ingredients, serving size, and price on Amazon.
View on Amazon →Reminder: Supplements are not a substitute for prescribed cholesterol medication. Do not stop or change a prescription without medical guidance.
❤️ More Heart-Health Supplement Options
Explore additional heart-health supplement options available on Amazon. Click through to view current pricing, ingredient labels, serving sizes, and customer reviews.


Reminder: Supplements are not a substitute for prescribed cholesterol medication. Do not stop or change a prescription without medical guidance.
12. FAQ
How much do PCSK9 inhibitors lower cholesterol?
On average, PCSK9 inhibitors lower LDL cholesterol by 50–60% when added to statin therapy. Repatha averages roughly 55–61%, while Praluent averages around 45–50%, with a range of 36–59% in FDA-reviewed trials. Some patients experience reductions above 70%.
Is Repatha or Praluent more effective?
Neither has been proven superior in a head-to-head cardiovascular outcomes trial. Repatha tends to produce slightly larger average LDL reductions in many datasets, but the difference is modest. The best choice depends on dosing preference, insurance coverage, cost, and tolerability.
How much do PCSK9 inhibitors cost per year?
List prices are approximately $5,850–$6,900 per year for Repatha and Praluent, depending on the product and dose. Manufacturer copay cards, direct-to-consumer programs, and Medicare Part D coverage can reduce out-of-pocket costs substantially. Repatha’s direct-to-consumer program offers a cash price of about $239 per month for eligible patients.
Do PCSK9 inhibitors reduce heart attacks and strokes?
Yes. In patients with established cardiovascular disease, both evolocumab (FOURIER) and alirocumab (ODYSSEY OUTCOMES) reduced the risk of major cardiovascular events by approximately 15% relative to placebo, on top of statin therapy.
Can I take a supplement instead of a PCSK9 inhibitor?
No. Dietary supplements are not FDA-approved to treat high cholesterol or reduce cardiovascular risk, and they are not substitutes for prescription lipid-lowering therapy. If you have familial hypercholesterolemia or established cardiovascular disease, discuss guideline-based treatment with a qualified clinician.
How often are PCSK9 inhibitors injected?
Repatha is injected every 2 weeks (140 mg) or once monthly (420 mg). Praluent is injected every 2 weeks (75 mg or 150 mg) or every 4 weeks (300 mg). Inclisiran is given twice yearly after initial dosing.
Are PCSK9 inhibitors covered by insurance?
Many commercial plans and Medicare Part D plans cover PCSK9 inhibitors, but prior authorization is common. Coverage and out-of-pocket costs vary by plan, deductible, and tier. Manufacturer copay cards and patient-assistance programs may help eligible patients.
13. Final Verdict
How much do PCSK9 inhibitors lower cholesterol? The practical answer is 50–60% additional LDL reduction on top of statin therapy—enough to move many high-risk patients from dangerously elevated LDL into a safer range. Repatha and Praluent are both effective, both have cardiovascular outcomes data, and neither has been proven clearly superior to the other.
Repatha may appeal to patients whose insurance covers it, who prefer a monthly dosing option, or who qualify for the direct-to-consumer cash price of about $239 per month. It has a slightly higher average LDL-lowering effect in many studies.
Praluent may appeal to patients who prefer flexible 2-week or 4-week dosing, whose insurance formulary prefers it, or who can access a lower negotiated price. Its average LDL reduction is somewhat lower, but it still produces clinically meaningful results and has proven cardiovascular benefit.
The most important step is not choosing between these two drugs in isolation. It is confirming—with a qualified healthcare professional—whether you meet the criteria for PCSK9 inhibitor therapy, whether lower-cost options have been optimized, and which product your insurance covers at the lowest out-of-pocket cost.
15. References
- U.S. Food and Drug Administration. REPATHA (evolocumab) prescribing information. Accessdata.fda.gov.
- U.S. Food and Drug Administration. PRALUENT (alirocumab) prescribing information. Accessdata.fda.gov.
- Patient-Centered Outcomes Research Institute (PCORI). PCSK9 Inhibitors Topic Brief.
- Sabatine MS, et al. FOURIER trial: evolocumab and cardiovascular outcomes. New England Journal of Medicine. Reported 15% relative risk reduction in major adverse cardiovascular events.
- ODYSSEY OUTCOMES Investigators. Alirocumab and cardiovascular outcomes after acute coronary syndrome. Hazard ratio 0.85 for major adverse cardiovascular events.
- Drugs.com. How much does Repatha cost? Updated February 27, 2026.
- Medical Times. PCSK9 inhibitor price reductions: Praluent annual price ~$5,850. September 30, 2026.
- DrugPatentWatch. Praluent average pharmacy cost. Updated March 17, 2026.
- Gunther B, et al. Cost-effectiveness of non-statin lipid-lowering therapies. SCAI 2026 Abstract.
- Rasch D, MD. PCSK9 Inhibitors: A Cardiologist’s Guide. Updated July 25, 2026.
- Meta-analysis: PCSK9 inhibitors reduce LDL-C by 50–70%. PMC.
- Injection-site reaction data: FOURIER trial and pooled alirocumab trials.

